HIPAA Compliance Gap Analysis Remediation Plan
A sample remediation plan that shows what comes after a gap analysis: how each gap is found, ranked, handed to someone, and closed out in a small practice.
Understanding the HIPAA Gap Analysis
A HIPAA gap analysis holds your program up against every HIPAA rule that applies to you, to find what is missing, half done, or never written down. It spans the full set of federal rules:
- Security Rule: Administrative safeguards (45 CFR §164.308), physical safeguards (§164.310), and technical safeguards (§164.312)
- Privacy Rule: How you may use and disclose protected health information, the minimum necessary standard, and what rights a patient has
- Breach Notification Rule: Who you have to tell after a breach of unsecured PHI, and when: the people affected, HHS, and the press, under §164.404
What you get back is a list of findings: the places where the practice does not yet meet a HIPAA rule. Each one goes into a remediation plan with the CFR it maps to, a risk level, the fix, the person who owns it, and a due date.
What a Remediation Plan Looks Like
After the gap analysis, each finding goes into a remediation plan. The table below shows the kind of findings a small practice tends to see. Yours will differ.
| Finding | CFR Reference | Risk Level | Remediation Action | Owner | Timeline |
|---|---|---|---|---|---|
| No documented Security Risk Assessment | §164.308(a)(1)(ii)(A) | High | Complete SRA using structured methodology | Privacy Officer | 30 days |
| Missing written policies and procedures | §164.316(a) | High | Draft and implement 38 required policies | Office Manager | 45 days |
| No staff training records on file | §164.308(a)(5)(i) | High | Enroll staff in training modules, document completion | HR Lead | 30 days |
| BAAs missing for 3 vendors | §164.502(e) | High | Execute digital BAAs for all PHI-touching vendors | Privacy Officer | 14 days |
| No breach notification procedure | §164.404(b) | Medium | Document incident response workflow | Privacy Officer | 21 days |
| Workstation screens visible to patients | §164.310(b) | Medium | Install privacy screens, reposition monitors | Office Manager | 7 days |
How the Remediation Process Works
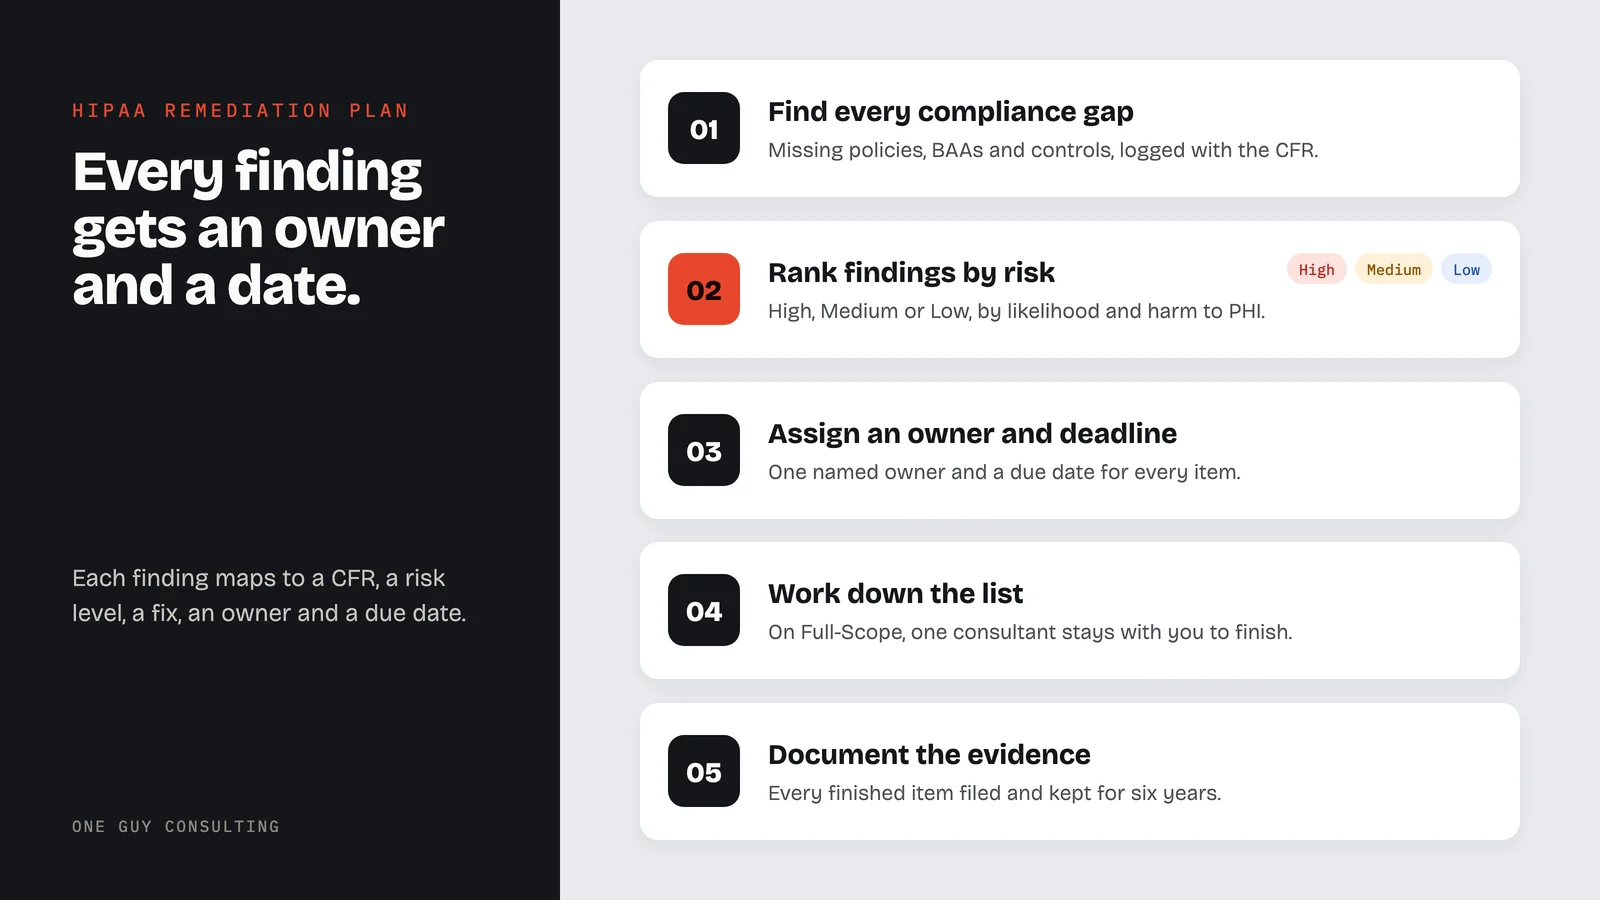
- 01
Gap Analysis Identifies All Compliance Gaps
We check every HIPAA rule against what you have now. Policies you lack, steps no one wrote down, training records with holes, BAAs no one signed, security controls no one set up: each is logged with the CFR it maps to.
- 02
Findings Ranked by Risk Severity
Each finding gets a risk level of High, Medium, or Low. That rests on how likely the issue is and how much it could hurt PHI. The high ones, such as a missing risk assessment or no policies at all, go first.
- 03
Each Finding Assigned an Owner and Deadline
Every item gets one named owner and a due date. That is what keeps a finding from sitting there for a year.
- 04
Implementation with Consulting Support
The practice works down the list. On the Full-Scope plan, one consultant stays with you to finish the risk assessment, draft the policies, run the training, and get BAAs signed.
- 05
Evidence Documented for Six-Year Retention
Every finished item, signed document, training record, and risk assessment output is filed and kept for the six years §164.530(j) calls for. That file is what you reach for if OCR ever audits you or opens a case.
What to Do If Your Clinic Has No Risk Assessment
If your clinic has no HIPAA risk assessment or written policies yet, start with a Security Risk Analysis now: identify where PHI is stored and transmitted, list your vendors and devices, document the main risks, then put the required policies and procedures in writing and assign someone responsible for security. For a step-by-step walkthrough, see how small clinics handle risk assessments.
The Security Rule at 45 CFR §164.308(a)(1)(ii)(A) says every covered entity and business associate has to run a risk assessment. Section §164.316(a) says the policies and procedures have to be in writing. Neither one waits until you have time.
Here is a practical starting sequence:
- Inventory your PHI. Where does electronic protected health information get made, come in, sit, and go out? Count your EHR, email, fax, cloud storage, and every phone or tablet.
- List your vendors. Name every one that handles PHI for you: your EHR, your billing company, cloud hosting, IT support, the shredding service. Each is one of your business associates, so each needs a signed Business Associate Agreement.
- Document the risks. For each system and each workflow, write down what could go wrong (someone gets in, a laptop walks off, ransomware) and what you have in place (passwords, encryption, locks).
- Write your policies. Start from policy templates and build the written set you need: who can get in, what to do when something breaks, how staff are trained, and how devices are handled.
- Assign a Security Officer. HIPAA calls for a named security official under §164.308(a)(2). It can be the owner, the office manager, or someone you bring in.
This content is for educational and informational purposes only and should not be construed as legal advice. Organizations should consult legal counsel for guidance specific to their situation.
HIPAA Gap Analysis and Remediation Questions
What do I do if my small clinic still does not have a HIPAA risk assessment or written policies?+
If your clinic has no HIPAA risk assessment or written policies yet, start with a Security Risk Analysis now: identify where PHI is stored and transmitted, list your vendors and devices, document the main risks, then put the required policies and procedures in writing and assign someone responsible for security. The Security Rule under 45 CFR §164.308(a)(1)(ii)(A) requires a risk assessment, and §164.316(a) requires written policies and procedures. These are not optional steps that can wait. Organizations should consult legal counsel for guidance specific to their situation.
What is the difference between a gap analysis and a risk assessment?+
A gap analysis compares your current compliance program against all HIPAA requirements to identify what is missing. It covers the Security Rule (§164.308, §164.310, §164.312), Privacy Rule, and Breach Notification Rule. A Security Risk Assessment under §164.308(a)(1)(ii)(A) focuses on identifying threats and vulnerabilities to the confidentiality, integrity, and availability of electronic protected health information. A gap analysis is broader in scope. A risk assessment is deeper on security threats. Most practices need both.
How long does remediation take for a small practice?+
With a structured remediation plan, remediation for a small practice takes weeks, not months. High-risk findings like missing risk assessments and absent written policies are addressed first. Medium-risk items like breach notification procedures and physical safeguard improvements follow. Low-risk items and records cleanup come last. Timelines vary depending on practice size, number of findings, and staff availability. Evidence of remediation must be retained for six years per §164.530(j).
What HIPAA compliance help does One Guy Consulting offer for small healthcare practices and business associates?+
One Guy Consulting offers full-scope HIPAA help for small practices and business associates, including a Security Risk Assessment under §164.308(a)(1)(ii)(A), gap analysis and remediation plans, custom policies and procedures per §164.316(a), staff training with tracking per §164.308(a)(5)(i), site and IT audits under §164.310 and §164.312, vendor and BAA management per §164.502(e), incident handling and breach notification support per §164.404(b), and audit-readiness support with records retention per §164.530(j). Everything is included in one flat annual rate with no per-user fees.
Learn More About HIPAA Compliance
Ready to Identify and Close Your Compliance Gaps?
Book a free 30-minute call. We will look at where you stand and walk you through what a gap analysis and a remediation plan would mean for your practice.